
A Post That Made Me Think
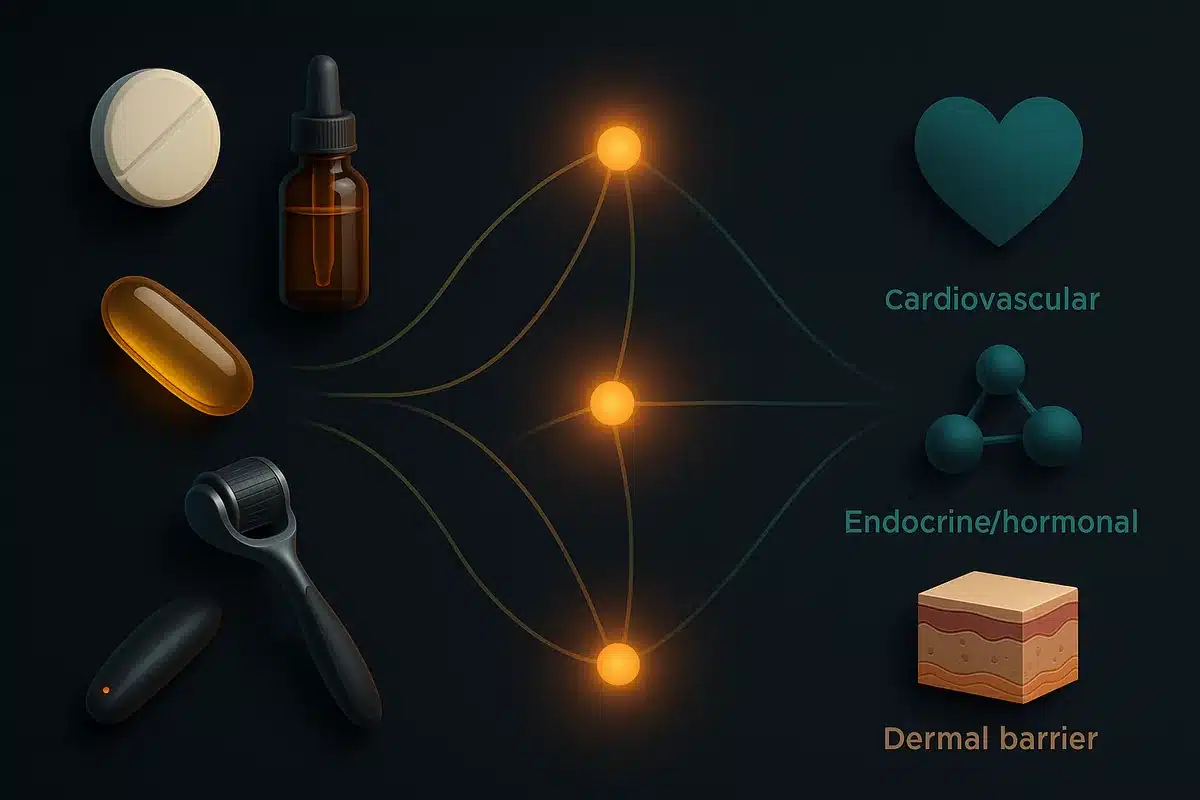
I came across a post on Reddit recently that stayed with me. A woman in her early twenties had shared her journey since being diagnosed with female pattern hair loss (FPHL) — a condition that, for many young women, arrives without warning and carries a weight far beyond the physical.7 She had clearly done her research. In the months since diagnosis, she had assembled what can only be described as a sophisticated treatment protocol: topical and oral minoxidil, a compounded topical dutasteride preparation applied nightly, weekly microneedling with a derma stamp, low-level laser therapy several times a week, pumpkin seed oil supplementation, a methylated prenatal multivitamin, daily scalp massage, and regular use of an antifungal shampoo.
She was not reckless. She was not uninformed. She was a young woman who had received a diagnosis that research consistently shows causes profound psychological distress — and she had done exactly what an intelligent, motivated person does when the healthcare system fails to offer adequate support: she found a community, read widely, and took action.7
And yet, reading through her post, I found myself thinking not about what she was doing, but about what was absent. Because in all of that careful planning, there was one thing that no online community — however knowledgeable its members — can provide: a structured framework for knowing whether any of it is working, or whether any of it may be quietly causing harm that has not yet surfaced.
What the Research Says About This Treatment Stack
Let us be clear from the outset: several elements of this type of protocol are supported by clinical evidence and, under appropriate professional supervision, may form part of a legitimate treatment approach. Minoxidil remains the first-line pharmacological treatment for FPHL.8 The concern here is not with the individual interventions, but with the absence of the monitoring infrastructure that makes using them together safe, interpretable, and accountable.
Oral Minoxidil and Cardiovascular Risk
Low-dose oral minoxidil has emerged as an increasingly popular off-label treatment for hair loss, and a growing evidence base supports its effectiveness. It is, however, a systemic arteriolar vasodilator — a cardiovascular drug whose hair growth effects were originally identified as a side effect — and its safety profile reflects that origin. A large multicenter study of 1,404 patients, the majority of whom were women, documented systemic adverse effects including fluid retention, tachycardia, and lightheadedness.2 A 2025 narrative review reported twelve cases of severe adverse events in women using low-dose oral minoxidil, including two cases of ischemic stroke and myocardial infarction, in patients with no prior history of cardiovascular disease.3
A pharmacovigilance analysis of the FDA Adverse Event Reporting System (FAERS) identified a statistically significant signal for pericardial effusion — fluid accumulation around the heart — at oral minoxidil doses of 1.25mg or less, with a reporting odds ratio of 16.41.1 These events are uncommon. But they are not hypothetical. And they are events for which, without any baseline cardiovascular monitoring, there is no early warning framework in place. If you take oral minoxidil and notice swollen ankles, a racing heartbeat, breathlessness or chest discomfort, see a doctor promptly.
Topical Dutasteride and Reproductive Safety
Dutasteride is a dual 5-alpha reductase inhibitor — more potent than finasteride, and with a substantially longer elimination half-life of approximately five weeks. As a compounded topical preparation, it has become increasingly accessible through telehealth platforms and compounding pharmacies. Its potential role in supporting hair density in certain presentations is an area of continuing research interest.
What is not in question is its reproductive safety classification. Dutasteride is contraindicated in women of reproductive age.4 The mechanism is well established: dihydrotestosterone (DHT) is essential for normal male foetal development, and dutasteride’s inhibition of both type I and type II 5-alpha reductase isoenzymes may cause congenital abnormalities in male foetuses following in-utero exposure. The compound can be absorbed through skin contact alone — so thoroughly so that women who are or may be pregnant are advised not to handle even the intact capsule form of the oral preparation.4
A real-world pharmacovigilance study from the Netherlands examined dispensing data across community pharmacies and found that a substantial proportion of women of reproductive age were receiving 5-alpha reductase inhibitor prescriptions without adequate concurrent contraception — a finding that prompted calls for additional risk minimisation measures beyond existing label warnings.5 When this compound is obtained through informal compounding channels, those institutional safeguards are absent entirely.
The Microneedling Amplifier
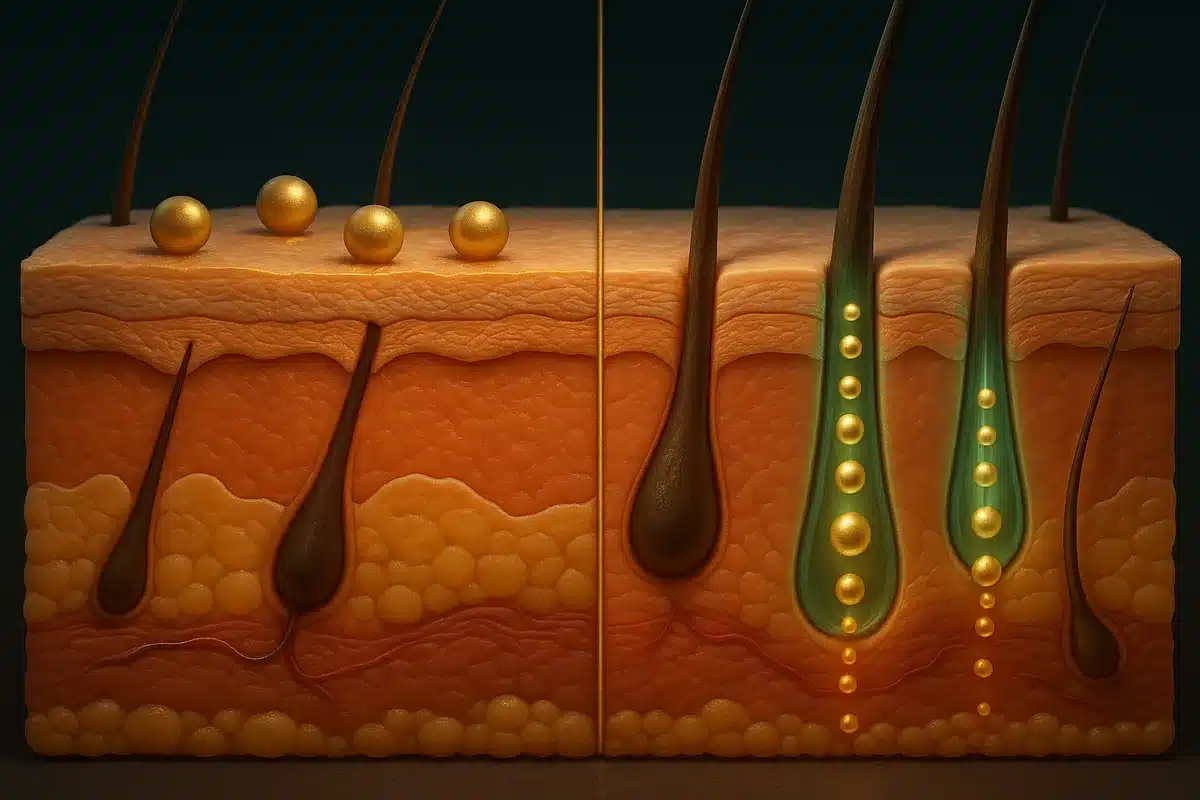
Perhaps the least discussed interaction in this type of protocol is the relationship between microneedling and whatever topical preparation follows it. Microneedling functions by creating controlled micro-injuries in the stratum corneum — the outermost skin barrier. These microchannels meaningfully increase the transdermal absorption of any compound applied to the scalp in the treatment window that follows. Research indicates that topical minoxidil has a baseline dermal absorption rate of only 0.3–4.5% of the applied dose under standard conditions; microneedling dramatically increases this figure by creating direct delivery channels into the dermis.6
When this amplification effect is applied to a topical dutasteride preparation, the systemic exposure from what is nominally a “topical” product may be substantially higher than either the prescribing information or the patient’s understanding would suggest. There are, to date, no published pharmacokinetic studies characterising systemic dutasteride levels following topical scalp application combined with regular microneedling. That absence of data is not, in itself, evidence of harm — but it is precisely the kind of uncertainty that a baseline monitoring framework exists to detect and contextualise.
The Gap That Communities Cannot Fill
The woman whose post prompted this piece is far from unusual. FPHL carries a significant and well-documented psychosocial burden: research consistently finds that 70% of affected women describe themselves as very to extremely upset about their hair loss, and 88% report that the condition negatively influences daily life.7 Younger patients — those in their twenties and thirties — experience significantly greater stigmatisation, poorer emotional functioning, and higher levels of anxiety than older cohorts.8 The distress is real, proportionate, and a legitimate driver of action.
Online communities form precisely in response to that distress. They offer what traditional healthcare so often does not: acknowledgement, shared experience, and actionable information. The pharmacological knowledge that circulates in these communities is genuinely sophisticated. Community members cite published studies, discuss dosing rationales, and share detailed longitudinal progress notes. The limitation is not intellectual — it is structural. No community, however well-informed, can provide what a clinical monitoring framework provides: an objective baseline taken at the moment of intervention, a standardised methodology for measuring change, and the capacity to detect movement in either direction before it becomes a clinical event.
The woman in that post had a “before” photograph. What she did not have was a trichoscopic baseline — a standardised, magnified, quantitative assessment of hair shaft diameter, follicular density, terminal-to-vellus hair ratio, and scalp condition taken at the point she began treatment. Without that, it is not possible to say, with any degree of objectivity, whether her protocol is producing improvement, has reached a plateau, or is masking subclinical regression behind the noise of other variables.9
What Structured Monitoring Changes
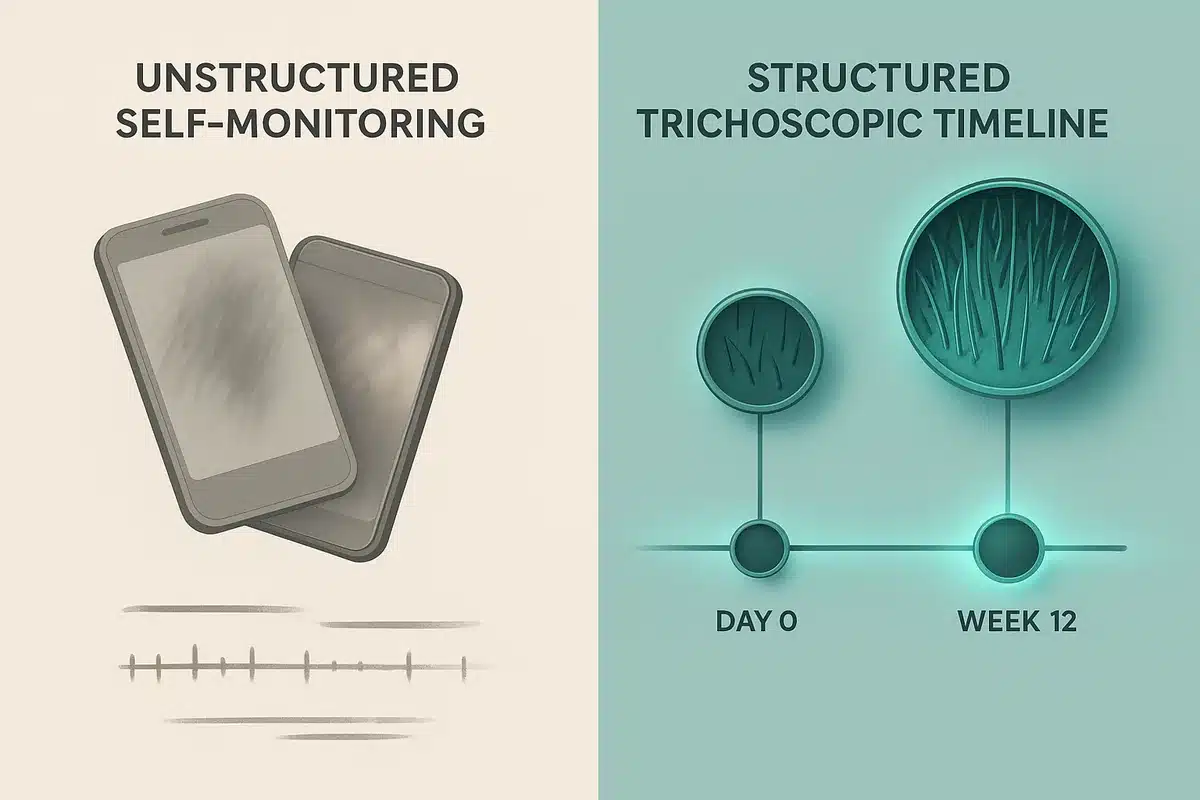
Trichoscopy, used longitudinally and at defined intervals, provides precisely this missing layer. A prospective clinical study confirmed trichoscopy as a sensitive method for monitoring treatment response in androgenetic alopecia, enabling objective measurement of terminal hair count, vellus hair count, total hair count, and the terminal-to-vellus ratio over time.9 When those measurements are taken at baseline and at structured follow-up points, the result is not just a clinical record — it is an evidence base that informs every subsequent decision about whether to continue, adjust, or question a protocol.
In practice this has two halves. A trichoscopic baseline is something a dermatologist can take before a protocol starts, or before another intervention is added. The home half is a record you keep yourself: photographs of the same scalp zones, taken the same way each time and dated, with a short note on how your scalp feels and what you changed. Each entry compounds the last. What emerges over time is not simply a collection of snapshots — it is a narrative, belonging entirely to you, that any GP or dermatologist can engage with meaningfully.
Scalp Score, the Orga Hair app, helps with that home half. Five short questions give you a free Scalp Score straight away, with no sign-up; the Photo Journal keeps your own photographs in date order so you can compare them side by side, and the wash-day check-in keeps your notes. It describes what your answers and photographs show; it does not measure density, diagnose, or tell you whether a medicine is working.
None of this replaces medical oversight — particularly where prescription compounds are involved. A record simply makes the gap between appointments smaller, the information richer, and the conversation with whoever prescribes more substantive. It is what turns a well-intentioned, research-informed protocol into something structured enough to be genuinely interpretable — to you, and to anyone you consult.
The Second Best Time
There is a saying — its origins more modern than most realise — that “the best time to plant a tree was 20 years ago. The second best time is now.” The same logic applies here. The best time to start a proper record may have been the day you first noticed something changing. If that moment has passed, the next best time is today — before another intervention is added, and before the only reference point available is a photograph taken in a bathroom mirror: a trichoscopic baseline from a dermatologist if you can arrange one, and your own dated photographs either way.
The woman in that Reddit post is motivated, informed, and taking her health seriously. What she deserves — and what anyone running a serious hair health protocol deserves — is a prescriber who knows the whole protocol, and a record that shows, with some degree of objectivity, whether it is working.
References
- Gupta AK, Talukder M, Venkataraman M, et al. Low-Dose Oral Minoxidil and Associated Adverse Events: Analyses of the FDA Adverse Event Reporting System (FAERS) With a Focus on Pericardial Effusions. J Am Acad Dermatol. 2024. Available at: https://pubmed.ncbi.nlm.nih.gov/39327649/
- Vañó-Galván S, Pirmez R, Hermosa-Gelbard A, et al. Safety of Low-Dose Oral Minoxidil for Hair Loss: A Multicenter Study of 1404 Patients. J Am Acad Dermatol. 2021;84(6):1644–1651. Available at: https://pubmed.ncbi.nlm.nih.gov/33639244/
- Sanabria B, et al. Characterization and Management of Adverse Events of Low-Dose Oral Minoxidil Treatment for Alopecia: A Narrative Review. J Clin Med. 2025;14(6):1805. Available at: https://www.mdpi.com/2077-0383/14/6/1805
- StatPearls. Dutasteride. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2024. Available at: https://www.ncbi.nlm.nih.gov/books/NBK603726/
- Teichert M, et al. Contraindicated Use of 5-Alpha-Reductase Inhibitors in Women. Br J Clin Pharmacol. 2017;83(5):1170–1175. Available at: https://pmc.ncbi.nlm.nih.gov/articles/PMC5237684/
- Pei Y, et al. Efficacy and Safety of Combined Microneedling Therapy for Androgenic Alopecia: A Systematic Review and Meta-Analysis of Randomized Clinical Trials. J Cosmet Dermatol. 2024;23:1598–1609. Available at: https://onlinelibrary.wiley.com/doi/10.1111/jocd.16186
- Vujovic A, Del Marmol V. The Female Pattern Hair Loss: Review of Etiopathogenesis and Diagnosis. BioMed Res Int. 2014;2014:767628. Available at: https://pmc.ncbi.nlm.nih.gov/articles/PMC4000932/
- Ramos PM, Miot HA. Female Pattern Hair Loss: A Clinical and Pathophysiological Review. An Bras Dermatol. 2015;90(4):529–543. Available at: https://pmc.ncbi.nlm.nih.gov/articles/PMC6322157/
- Yıldırım İ, et al. The Value of Trichoscopy in the Follow-up of Treatment Response in Patients With Androgenetic Alopecia. Dermatol Pract Concept. 2024. Available at: https://pmc.ncbi.nlm.nih.gov/articles/PMC10868879/



